

Healthcare sector represented by a premium conceptual abstract graphic on a reflective white background illustrating healthcare care-governability. A sapphire glass network on the right carries a continuous, glowing teal EKG pulse representing clinical operations, while an incoming red threat stream is cleanly intercepted and isolated by a vertical brushed-titanium block outlined in a vibrant neon light-blue glow, ensuring care continuity remains entirely stable and unaffected on the left.Healthcare sector represented by a premium conceptual abstract graphic on a reflective white background illustrating healthcare care-governability. A sapphire glass network on the right carries a continuous, glowing teal EKG pulse representing clinical operations, while an incoming red threat stream is cleanly intercepted and isolated by a vertical brushed-titanium block outlined in a vibrant neon light-blue glow, ensuring care continuity remains entirely stable and unaffected on the left.

Healthcare Sector

Care continuity when clinical systems become uncertain

Care delivery under degraded conditions

Patients continue to arrive, clinicians continue to make decisions, and pharmacy and administrative teams continue to move medication, eligibility and discharge work through the day. A cyber incident becomes clinically significant when the systems supporting those decisions are delayed, incomplete or unavailable.

A prescription cannot be verified quickly enough. A patient record is accessible but may no longer be current. A vendor portal stops returning eligibility data. Teams create workarounds because care cannot wait, yet every workaround removes context, consumes staff time and increases the chance of inconsistency.

A hospital does not need to close for a cyberattack to affect care. The decisive question is whether clinicians and operational teams can preserve safe care while affected systems are isolated and the full incident picture remains incomplete.

A hospital may remain open.
Safe care still depends on information that clinicians can use and verify.

When a vendor incident becomes a care-continuity event

Change Healthcare made the healthcare control problem impossible to ignore. It was not simply a technology outage at a supplier. It became a system-wide healthcare event. Claims processing slowed. Eligibility verification was disrupted. Pharmacy and payment workflows were affected. Providers faced cash-flow pressure. Patients experienced delays and friction at points where healthcare should feel dependable.

The American Hospital Association published a survey of nearly 1,000 hospitals. In this survey, 74% reported a direct impact on patient care, whilst 94% documented financial consequences stemming from the Change Healthcare cyberattack. This metric underscores the true healthcare pattern: an external compromise can easily strip a hospital of its operational room. A mission-critical provider sitting outside your walls can still dictate what happens within them.

The long tail matters as well. In 2025, the US Department of Health and Human Services listed approximately 192.7 million individuals as impacted by the Change Healthcare breach. Even after systems return, exposed data can continue to shape patient trust, regulatory scrutiny and institutional confidence.

What maturity can hide

Healthcare organisations are often very good at keeping care moving through disruption. Clinicians improvise, departments create manual workarounds and administrative teams rebuild processes that normally happen automatically. That operational strength is essential, but it can also hide how quickly the quality of the working environment is deteriorating.

A workaround consumes time and separates information from its normal checks. Medication, identity, eligibility, imaging, scheduling and discharge decisions may still be made, but with more manual verification and less shared context. The longer that condition persists, the more likely temporary measures are to become the operating model for the incident.

Healthcare is a chain of time-sensitive decisions supported by electronic health records, pharmacy systems, imaging, identity, virtual infrastructure, remote support and external vendors. A cyber incident does not have to close the hospital to affect care. It can reduce the speed, completeness and defensibility of decisions while the hospital remains visibly open.

What this feels like in healthcare

Healthcare leaders recognise the pressure because it rarely arrives as one clean failure. It arrives as many small breakdowns at the same time.

  • A pharmacy team cannot verify a prescription quickly enough, so the patient experience becomes slower and more uncertain.
  • An eligibility or prior-authorisation process stalls, so treatment pathways become harder to coordinate and explain.
  • Clinicians move to paper, not because paper is resilient, but because the digital record can no longer be fully trusted or reached.
  • Administrative teams work longer hours to recreate flows that a vendor platform normally handles invisibly.
  • A supplier connection, remote support path or server environment becomes suspect, but disconnecting it may affect care systems that are still needed.
  • Patients, insurers, pharmacies, regulators, clinicians and executives all need answers before the incident team has complete facts.

This is why the phrase “the hospital is still open” can be misleading. Healthcare can continue while governance deteriorates. A healthcare organisation may still be treating patients, but each workaround consumes time, staff attention, clinical confidence and leadership capacity. At that point, the incident is no longer just about whether systems are available. It is about whether care decisions are still supported by trusted information.

Why healthcare decisions deteriorate differently

Healthcare cannot pause while certainty is rebuilt. Patients continue to arrive, medication must still be administered and diagnostic, transfer and discharge decisions remain time-sensitive. The operational cost of delay is therefore measured in clinical workload and patient consequence, not only in unavailable technology.

An isolation decision may protect the wider environment while removing a system that a department still needs. Continuing without restriction may preserve access in the short term while giving the attacker more room to reach patient data, shared services or virtual infrastructure.

The executive and clinical task is to preserve a safe care pathway, even if it is narrower or slower than normal. That requires pre-agreed alternatives for critical workflows, clear authority to isolate affected access and a way to verify the information clinicians continue to use.

Healthcare containment succeeds when it reduces the attacker's reach before clinical teams are forced to choose between delayed care and care delivered with insufficient information.

Healthcare control is care-governability.
Not simply system availability.

The leadership dilemma

The central healthcare dilemma is simple to state and hard to execute: "WHAT CAN WE ISOLATE WITHOUT STOPPING CARE?"

That question should not be discovered for the first time during a live ransomware incident. The answer depends on operational knowledge that must already be mapped: which systems support emergency care, which vendor routes support pharmacy and eligibility, which server environments support critical applications, which identity paths allow remote support, which data stores contain sensitive patient information, and which workloads can safely move into degraded operation.

Under pressure, leadership cannot wait for perfect certainty. But it also cannot act blindly. Disconnect too little, and the attacker may keep moving. Disconnect too much, and your organisation may widen the impact by its own response. The leadership task is to preserve enough operational room to continue care while reducing the attacker’s room to move.
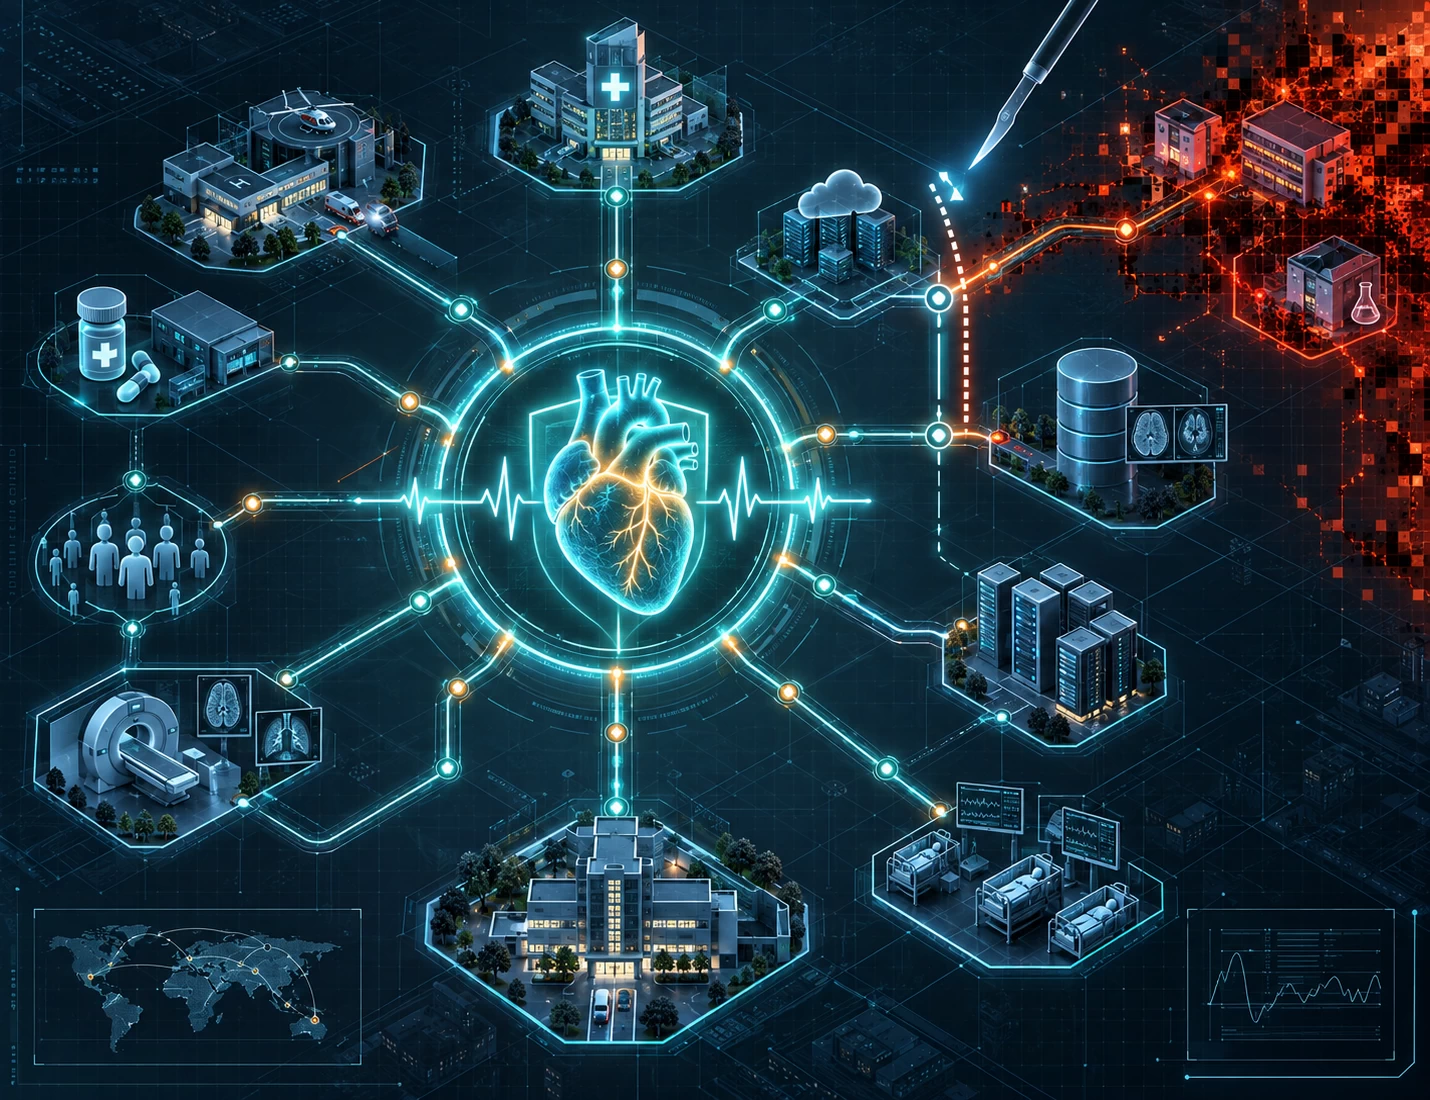
A modern digital blueprint illustrating the healthcare security dilemma of network isolation versus patient care. In the center, a glowing teal EKG line represents continuous emergency operations. Branching outward are interconnected network nodes representing pharmacy routes, server workloads, and data stores. From one side, a dark orange-red pixelated grid represents creeping ransomware. A precise, dotted boundary line and digital cursor hover between the two zones, visualizing the high-stakes decision of where to surgically disconnect the network to contain the threat without shutting down critical clinical care.

When containment is late

Late containment increases the number of clinical dependencies that must be questioned. A compromised account can reach additional systems. A remote session can become deeper server access. Shared storage or virtual infrastructure can place several clinical and administrative workloads inside the same investigation.

The consequence appears in care operations before every technical fact is known. More records require verification, more departments move to manual work, more vendor connections need review and more recovery points must be checked before systems can safely return.

Each additional dependency makes clinical coordination slower. Pharmacy, imaging, admissions, discharge and revenue-cycle teams may all remain active, but they spend more time confirming information and less time using it. Communication also becomes harder because the organisation cannot yet state which records, services or connections were affected.

Hospitals rarely stop treating patients.
The greater danger is a gradual loss of reliable clinical context while care continues.

What early containment changes

Early containment preserves clinical options. Restricting harmful activity before it reaches more accounts, data stores, servers or virtual workloads reduces the number of care processes that have to move into emergency fallback.

The benefit is practical. Clinical and operational teams have more time to identify which services can remain available, which departments need an alternative workflow and which records or interfaces require validation before normal use resumes.

Early containment does not make care delivery frictionless, and it does not replace clinical continuity planning. It helps keep the technical problem smaller so that clinicians and executives face fewer unsafe compromises while investigation and recovery continue.

In healthcare, the value of containment is the preservation of usable care pathways
before digital disruption begins to dictate clinical choices.

How our containment platform supports healthcare control

Our containment platform becomes relevant when malicious activity has entered the environment and your organisation needs to restrict the paths through which harm can spread without removing more clinical capacity than the situation requires.

Ransomware Containment is the platform’s central containment engine. It adds an operational control layer to your existing prevention, detection, response and recovery capabilities by detecting illegitimate encryption and isolating the responsible user, session or device.

Additional Server Intrusion Protection and Virtual Server Protection features extend that control to compromised server access and attacks directed at supported hypervisor environments. Together, these capabilities help security and infrastructure teams translate a credible signal and an authorised decision into proportionate containment action while the full incident picture is still developing.

For healthcare organisations, the practical value lies in preserving more opportunity to contain harmful activity before additional records, systems and shared infrastructure are affected, or care teams are forced into increasingly unsafe fallback procedures.

Containment does not remove the need for investigation, recovery, communication or executive governance. It preserves more operational room in which those activities can take place before the incident becomes harder to control.

How our platform protects healthcare operations

  • Ransomware Containment:
    Our platform agentlessly monitors file activity across the protected data environment. Once illegitimate encryption begins, it detects the activity and isolates the responsible user, session or device, helping prevent encryption from spreading across file shares and data stores on which healthcare services depend.
  • Additional Server Intrusion Protection:
    SIP extends the platform’s protection to server-level intrusion involving compromised administrative credentials and the misuse of remote-access or scheduled-task mechanisms. It helps detect and contain compromised server access before an intruder can continue reconnaissance, move laterally, disable security controls, stage ransomware or exfiltrate data. This is especially relevant to remote support paths, identity-adjacent systems and servers supporting critical healthcare operations.
  • Additional Virtual Server Protection:
    VSP extends the platform’s protection to supported VMware, vSphere, ESXi and Hyper-V hypervisor environments. Depending on the supported platform and configuration, it can provide additional protection for critical administrative paths, host processes, datastores, virtual-machine files and relevant configuration layers. This matters when many clinical and administrative workloads depend on the same virtual infrastructure.

What healthcare teams should establish before an incident

Healthcare readiness extends beyond a technology test. Your clinical, operational, security and infrastructure teams should know which systems support time-critical care, which vendor and remote-access routes can be restricted, how current patient information will be verified and who may authorise isolation when the full impact is still uncertain.

Those questions require architecture review, continuity planning, clinical input and technical validation. They should be resolved before an incident forces staff to invent alternatives during care delivery.

Our remote ransomware resilience assessment has a deliberately narrower scope. In a controlled sandbox, it compares file-encryption scenarios with your existing security controls left active, first without Ransomware Containment enabled and then with it enabled. It tests whether active encryption can be isolated before it spreads further. It does not test SIP, VSP, lateral movement, data exfiltration, vendor dependencies, clinical continuity or executive decision-making.

The wider healthcare question remains: if a cyberattack affects the systems supporting care, can your organisation preserve the clinical processes that must continue while isolating the activity that must stop?

Run a resilience assessment.

For organisations that want a focused, practical comparison, we can run a free remote ransomware resilience assessment in a controlled sandbox environment. With your existing security controls left active, we use several ransomware variants to observe how the current security stack responds once encryption begins. We then repeat the same scenarios with our ransomware-containment layer enabled and compare the outcomes.

DISCOVER HOW OUR PLATFORM WORKSRUN A RESILIENCE ASSESSMENT

Further readings

